BPC-157 vs GHK-Cu
The distinction that mattersInjected GHK-Cu is usually bought inside the three-peptide "GLOW" blend alongside BPC-157 and TB-500, and forum reports credit or blame "GHK-Cu" for whatever the blend did. No published human trial has tested that combination, or any of its parts by injection, so reasoning from those reports assigns both effects and side effects to the wrong molecule — and GHK-Cu is the only one of the three that carries a metal ion.
These are not equivalent in evidence GHK-Cu is rated 3/5 and BPC-157 is rated 1/5 — a gap of 2 levels on our scale. Similar marketing does not mean similar proof.
| BPC-157 Research Use Only | GHK-Cu Cosmetic Ingredient | |
|---|---|---|
| Evidence rating |
1/5 Minimal
Evidence rating 1 out of 5: Minimal
|
3/5 Moderate
Evidence rating 3 out of 5: Moderate
|
| Regulatory status | Not approved anywhere. Its US pharmacy-compounding status moved twice in 2026 (see the dated record below); it remains an unapproved drug. WADA-prohibited since 2022. | Established cosmetic ingredient with human topical data. Injectable use is unapproved and unstudied. |
| Category | Healing & Tissue Repair | Skin & Cosmetic |
| Drug class | Synthetic pentadecapeptide derived from a sequence in human gastric juice protein BPC | Naturally occurring copper-binding tripeptide |
| Route | No approved route. Research and grey-market use is mostly subcutaneous, intramuscular or oral; the small published human literature used rectal enema, intra-articular injection, intravesical instillation and intravenous infusion, and the first randomised trial uses subcutaneous injection. | Topical (well studied); injectable (not studied) |
| Half-life | Not established in humans. In rats and dogs the plasma elimination half-life of the intact peptide is well under thirty minutes with linear, dose-proportional kinetics, and intramuscular bioavailability is roughly 14-51% depending on species; the two-person human infusion pilot was consistent with rapid clearance. Reported biological effects last hours to days, a mismatch no one has explained. | Commonly quoted as 30–60 minutes — that figure is an estimate repeated by suppliers and search summaries, not a measurement, and the same sources elsewhere give 1–2 hours or 4. No human pharmacokinetic study of GHK-Cu has been published for any route, so there is no measured half-life to report. What is established: rat work shows the tripeptide is cleared from plasma and broken to the dipeptide His-Lys, and once the peptide bonds are cut the copper does not leave with it but transfers to albumin, so the copper outlasts the peptide by far. Endogenous plasma GHK falls with age, but that is a concentration, not a half-life. |
| Sequence length | 15 residues | 3 residues |
| Molecular weight | 1,419.6 Da | 401.9 Da |
| Studied in | Extensive rodent models of tendon, ligament, muscle, bone, gut, liver, nerve and vascular injury, with more than 80% of the published literature coming from a single affiliated group at the University of Zagreb. Human exposure is small and almost entirely uncontrolled: a Pliva programme in inflammatory bowel disease (PL 14736) delivered as a rectal enema — a phase 1 in healthy volunteers and a randomised placebo-controlled phase 2 in ulcerative colitis, both reported only as meeting abstracts, the phase 2 showing no separation from placebo — a separate oral-tablet phase 1 that closed without posting results, and three small pilot reports covering intra-articular injection for knee pain, intravesical instillation for interstitial cystitis, and intravenous infusion in two people. A randomised placebo-controlled phase 2 in acute hamstring strain began recruiting in 2026. | A handful of small controlled human studies: a randomised, evaluator-blinded, vehicle-controlled trial of a copper tripeptide gel in diabetic foot ulcers (whose larger 511-patient successor failed), a maker-funded 8-week split-face wrinkle trial in 40 women, a small trial after laser resurfacing that was negative on blinded measures, and an 18-person eyebrow study. The cosmetic facial and eye-cream results were reported as 2002 conference abstracts rather than papers, and no controlled trial supports GHK-Cu alone for scalp hair. The bulk of the literature is fibroblast and keratinocyte culture plus rodent wound, lung and liver models. No controlled human study of any injected route. |
| Who should avoid it |
|
|
| Legal status | Not an approved drug in any country, and not a lawful dietary supplement. Sold under "research use only" labelling that confers no legality for human use. Whether a US pharmacy may compound it is a separate, moving question, recorded with dates below; no answer to it makes a research-use vial lawful to sell for human use. | Lawful as a cosmetic ingredient. Injectable preparations are unapproved. |
Benefits — BPC-157
- Consistent tendon and ligament healing in rodents
Multiple animal models show accelerated tendon-to-bone healing and improved biomechanical strength. The animal literature is genuinely large and internally consistent.
- Gut protection in animal models
Protects against NSAID-induced and other experimental gut injury in rodents, which is where the compound originated.
- Angiogenic activity
Promotes new blood-vessel formation in preclinical models — the likely common mechanism behind the varied healing effects.
- Low acute toxicity in animals
Rodent toxicology has not identified a clear toxic dose, though this says little about chronic human exposure.
- Closure of surgically created gut fistulas in rats
More specific than general mucosal protection. In the fistula work FDA summarised for its own review, colocutaneous fistulas in treated rats were about 40% smaller than vehicle controls from the third day after surgery and had closed macroscopically by day 28, while vehicle fistulas had shrunk by under a quarter. That is a hard surgical endpoint rather than a symptom score, which is what makes it interesting — but FDA also noted no supporting histopathology, no dose-response (two dose levels gave the same result), no test of treatment started later after the injury, and it comes from the same affiliated group as most of the literature, with no independent replication and no human counterpart.
Benefits — GHK-Cu
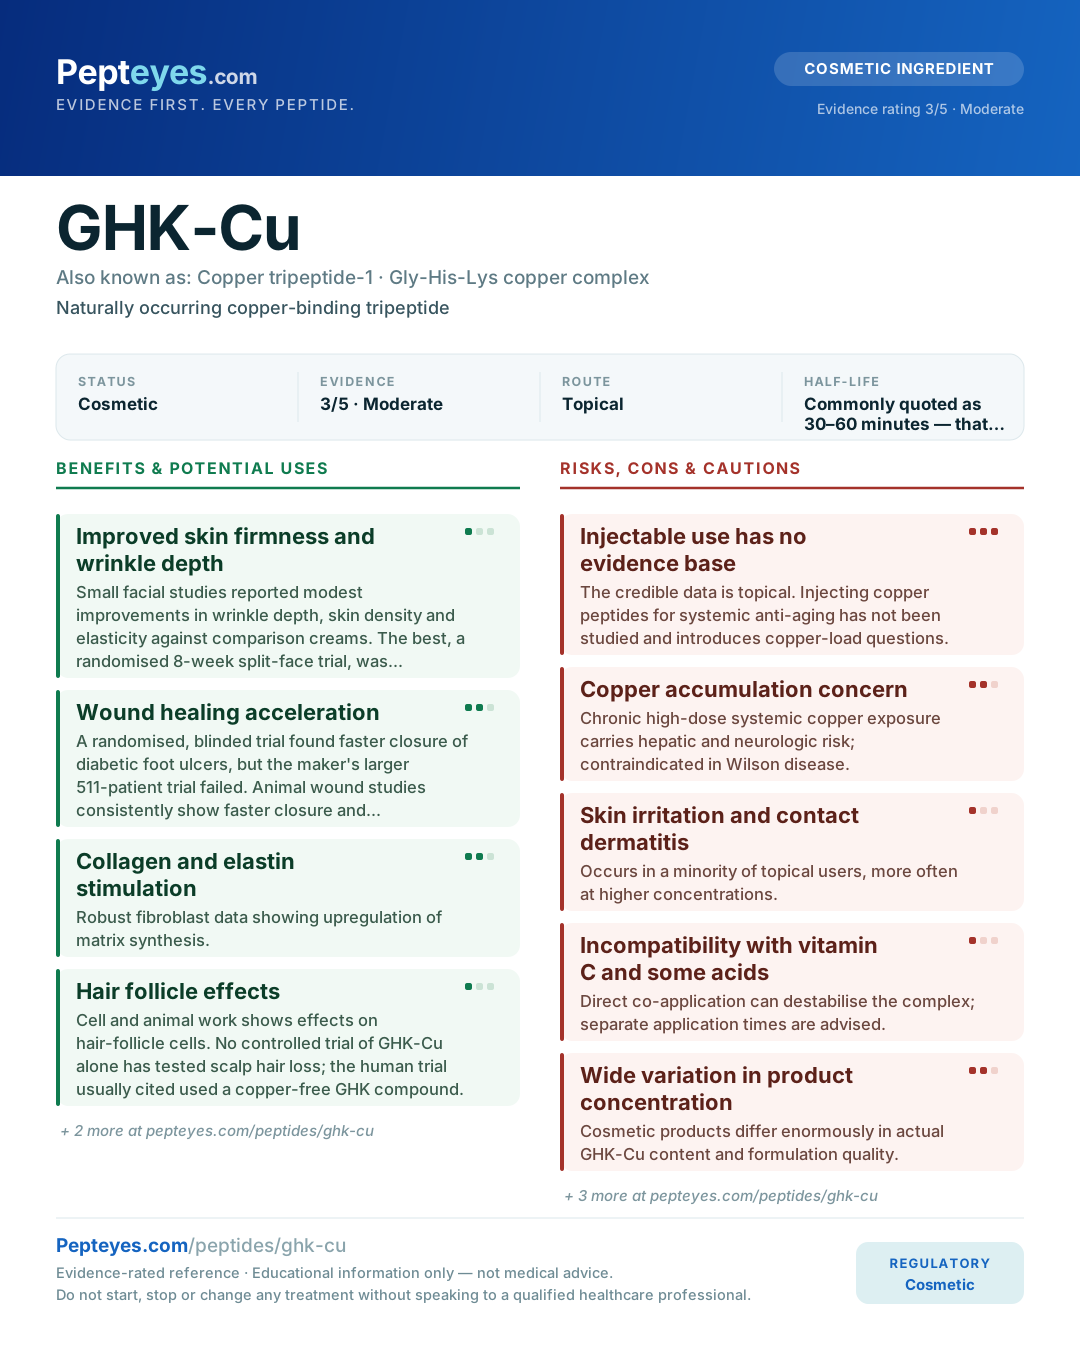
- Improved skin firmness and wrinkle depth
Small facial studies reported modest improvements in wrinkle depth, skin density and elasticity against comparison creams. The best, a randomised 8-week split-face trial, was maker-funded and could not separate GHK-Cu from its carrier; the older cream studies exist only as conference abstracts.
- Wound healing acceleration
A randomised, blinded trial found faster closure of diabetic foot ulcers, but the maker's larger 511-patient trial failed. Animal wound studies consistently show faster closure and better-organised collagen.
- Collagen and elastin stimulation
Robust fibroblast data showing upregulation of matrix synthesis.
- Hair follicle effects
Cell and animal work shows effects on hair-follicle cells. No controlled trial of GHK-Cu alone has tested scalp hair loss; the human trial usually cited used a copper-free GHK compound.
- Antioxidant and anti-inflammatory activity
Reduces oxidative damage markers in laboratory models.
Risks & cons — BPC-157
- No published randomized human trials
Every efficacy claim made for BPC-157 in humans is extrapolated from rodents or drawn from anecdote. This is the central fact about it.
- Angiogenesis cuts both ways
The same new-blood-vessel formation that helps a tendon heal is a mechanism tumours depend on. There is no data on use in people with occult or prior malignancy.
- The safety findings behind the 2023 listing were never answered
FDA reviewers judged the substance not well characterised: no control of specified impurities, aggregates, bioburden or endotoxin on a certificate of analysis, immunogenicity risk that rises for injected routes, and no identified molecular target. The listing that followed has since been withdrawn, but no new data resolved those findings — the position changed, the evidence did not.
- Product quality is frequently poor
Independent testing of grey-market peptide vials has repeatedly found incorrect content, degradation products, and bacterial contamination.
- Unknown long-term effects
No chronic exposure data at all. Users are the study population.
Risks & cons — GHK-Cu
- Injectable use has no evidence base
The credible data is topical. Injecting copper peptides for systemic anti-aging has not been studied and introduces copper-load questions.
- Copper accumulation concern
Chronic high-dose systemic copper exposure carries hepatic and neurologic risk; contraindicated in Wilson disease.
- Skin irritation and contact dermatitis
Occurs in a minority of topical users, more often at higher concentrations.
- Incompatibility with vitamin C and some acids
Direct co-application can destabilise the complex; separate application times are advised.
- Wide variation in product concentration
Cosmetic products differ enormously in actual GHK-Cu content and formulation quality.

A comparison is not a recommendation. Neither column is being suggested for you. Which — if either — is appropriate depends on your diagnosis, history and medications, and that is a conversation for a qualified clinician.