Supplied as a lyophilised powder to reconstitute
Growth Hormone Axis
At a glance
Ten answers, each one line. Open any row for the detail behind it.
What it does The compound that opened up the whole GHS field — it led directly to the discovery of the…
The compound that opened up the whole GHS field — it led directly to the discovery of the ghrelin receptor. As a therapy it is crude: powerful hunger stimulation and hormonal cross-talk made it impractical.
Half-life ~2.5 h elimination after IV in healthy men; the short figures… — Documented
~2.5 h elimination after IV in healthy men; the short figures quoted elsewhere are its ~8 min distribution phase.
Typical studied dose None established. No dose has ever been set for a human being, because… — Nothing established
None established. No dose has ever been set for a human being, because the studies that would set one have not been done. Any figure circulating for this compound was chosen by somebody selling it or by somebody guessing.
How often it is used No schedule exists. Cycles and intervals quoted for this compound come… — Nothing established
No schedule exists. Cycles and intervals quoted for this compound come from forums rather than from any study, and they vary because nothing anchors them.
How it is taken Subcutaneous (research) — Documented
Subcutaneous (research)
Main side effects No approved use anywhere · Unregulated supply · Intense hunger — Carries serious risk
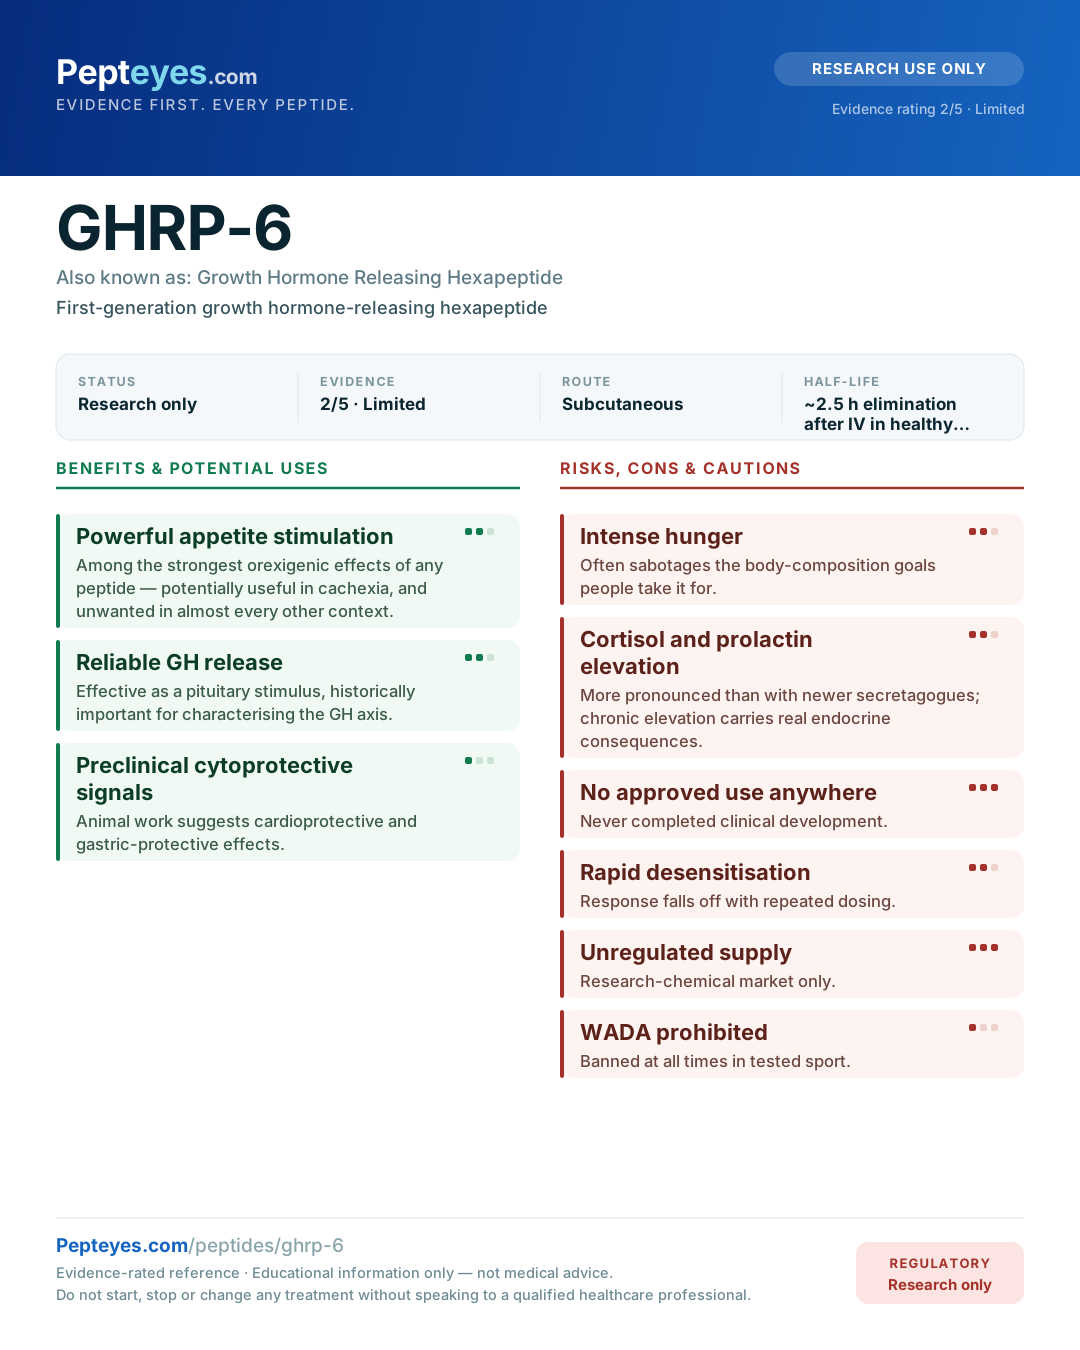
No approved use anywhere — Never completed clinical development.
Unregulated supply — Research-chemical market only.
Intense hunger — Often sabotages the body-composition goals people take it for.
Storage before mixing As a sealed lyophilised powder, refrigerated is typical and a freezer…
As a sealed lyophilised powder, refrigerated is typical and a freezer suits long storage; both should be dark and dry. A dry powder tolerates a few days out of the cold far better than anything in solution — which is why it ships that way.
Shelf life after mixing Once mixed it is refrigerated and treated as short-lived. Bacteriostatic…
Once mixed it is refrigerated and treated as short-lived. Bacteriostatic water contains a preservative and buys the longer window; sterile water contains none and buys a much shorter one. Peptides in solution also degrade on their own, so the container is only half the question.
Evidence level 2/5 · Limited — Nothing established
Preclinical work plus scattered human reports, uncontrolled use, or negative trials.
Regulatory status Research Use Only — Nothing established
Not approved. Superseded by more selective secretagogues; largely of historical and research interest. Not approved for human use in any major market.
Overview
The compound that opened up the whole GHS field — it led directly to the discovery of the ghrelin receptor. As a therapy it is crude: powerful hunger stimulation and hormonal cross-talk made it impractical.
Not approved for human use anywhereNo approval anywhere for human use. Sold under research-use labelling. Not approved for human use in any major market.
| Regulatory status | Not approved. Superseded by more selective secretagogues; largely of historical and research interest. |
|---|---|
| Drug class | First-generation growth hormone-releasing hexapeptide |
| Route | Subcutaneous (research) |
| Half-life | ~2.5 h elimination after IV in healthy men; the short figures quoted elsewhere are its ~8 min distribution phase. |
| Evidence rating |
2/5 Limited
Evidence rating 2 out of 5: Limited
Preclinical work plus scattered human reports, uncontrolled use, or negative trials. |
| Studied in | Extensive endocrine pharmacology research; small cardioprotection studies; no completed therapeutic development program. |
GHRP-6 sequence & structure
GHRP-6 is a 6-residue linear peptide with a C-terminal amide, carrying D-amino acid substitutions; molecular weight 873.03 Da.
lowercase = D-amino acid
Also called [His1,Lys6]-GHRP, SK&F-110679 and Hexapeptide-2. The 873.03 Da figure is the free base; vendors supply the acetate or TFA salt, so as-supplied weight is higher. PubChem holds two other records with the same connectivity but incomplete stereochemistry (CID 4345065, no stereocentres defined, InChIKey ...-UHFFFAOYSA-N; CID 5486806, Phe5 undefined, ...-PXILECETSA-N) — Wikipedia and the IUPHAR/BPS Guide to Pharmacology link to those, and the IUPHAR ligand 1093 record mislabels the N-terminus as methylated His (Me-His), which is not part of GHRP-6, so neither is used here. CAS 145177-42-0 appears only as a PubChem depositor synonym; 87616-84-0 is the number carried by ChemIDplus, DrugBank, EPA DSSTox and FDA GSRS. DrugBank DB18238 was confirmed through PubChem's cross-reference (DrugBank itself blocks automated fetches).
Record confidence: high — two independent authoritative sources agree on the sequence and modifications. Every sequence on the site is listed with its sources on the peptide sequences index.
How it works
Ghrelin receptor agonism with substantial off-target activation of ACTH/cortisol and prolactin release, plus strong central appetite stimulation.
Evidence base
Rated 2 of 5 — Limited. Preclinical work plus scattered human reports, uncontrolled use, or negative trials.
- Historically important research tool; no therapeutic evidence base.
Benefits and risks, weighed against the evidence
Every entry below carries the strength of the evidence behind it — three bars for strong human data, two for moderate, one for preliminary or preclinical work. The two columns are not equal by design: where a compound has more documented risk than demonstrated benefit, the lists say so.
Reported benefits
3 entries
-
Powerful appetite stimulation
Among the strongest orexigenic effects of any peptide — potentially useful in cachexia, and unwanted in almost every other context.
Evidence: Moderate evidence -
Reliable GH release
Effective as a pituitary stimulus, historically important for characterising the GH axis.
Evidence: Moderate evidence -
Preclinical cytoprotective signals
Animal work suggests cardioprotective and gastric-protective effects.
Evidence: Preliminary
Risks and cautions
6 entries · 2 serious or common
-
Intense hunger
Often sabotages the body-composition goals people take it for.
Evidence: Moderate evidence -
Cortisol and prolactin elevation
More pronounced than with newer secretagogues; chronic elevation carries real endocrine consequences.
Evidence: Moderate evidence -
No approved use anywhere
Never completed clinical development.
Evidence: Serious -
Rapid desensitisation
Response falls off with repeated dosing.
Evidence: Moderate evidence -
Unregulated supply
Research-chemical market only.
Evidence: Serious -
WADA prohibited
Banned at all times in tested sport.
Evidence: Minor
Counts are not a score. A single serious risk can outweigh several well-supported benefits, and a long benefit list built on preclinical work outweighs nothing at all.
Opinion — what people actually report
5 themes · 1 reported benefit · 3 reported problems
This is the weakest tier on this site. These are themes drawn from public discussion — forums, subreddits and patient threads — not from trials. There is no control group, no denominator, and no way to confirm that what someone injected matched its label. People post when a result is dramatic and when something goes wrong, and rarely when nothing happens, so treat everything below as a description of the conversation rather than of the compound. The bars count how often a thing is said, not how well it is supported.
-
Hunger described as extreme Reported problem. Dominant theme: Comes up in most discussions of this compound.
The single most reported effect, well ahead of anything else. Frequently characterised as uncontrollable and as the reason people abandon it.
-
Deliberately used to force appetite Reported benefit. Recurring: Raised regularly, though not by everyone.
The mirror image — people bulking or struggling to eat enough use it precisely for the effect others quit over.
-
The dirtiest of the three on cortisol and prolactin Reported problem. Dominant theme: Comes up in most discussions of this compound.
Consistently ranked worst in the class on this, which is why it has largely been displaced by ipamorelin in clinic use.
-
Heavy water retention Reported problem. Recurring: Raised regularly, though not by everyone.
Puffiness and weight gain that posters attribute to fluid rather than tissue.
-
Increasingly seen as the outdated option Practical note. Recurring: Raised regularly, though not by everyone.
Discussion often frames it as what people used before better-tolerated alternatives existed.
Where the reports and the evidence part ways
The appetite effect is genuine and mechanistically expected — this is a ghrelin receptor agonist, and ghrelin is the hunger hormone. That part of the community account is solid. Everything downstream is not: no human trials support the muscle, recovery or anti-ageing uses, and the compound never advanced as a therapeutic. The community's own hierarchy — GHRP-6 hungriest and least selective, GHRP-2 intermediate, ipamorelin cleanest — matches the receptor data reasonably well, which is an unusual case of forum consensus tracking pharmacology accurately while saying nothing about whether any of them work for the intended purpose.
Cheat sheet
The full sheet, all 77 compounds →The community reference numbers for this compound — reconstitution, working dose, cycle and bloodwork. Research and education only, not medical advice, and not part of the evidence-rated monograph above. Doses assume a 1mL / 100-unit insulin syringe — the calculator does the units for you.
Protocol overview
Dosing & reconstitution 5 mg vial
| WEEK/PHASE | DOSE PER INJECTION | UNITS PER INJECTION |
|---|---|---|
| Weeks 1 to 2 | 100 mcg | 1 units (0.01 mL) |
| Weeks 3 to 4 | 200 mcg | 2 units (0.02 mL) |
| Weeks 5 to 12 | 300 mcg | 3 units (0.03 mL) |
Frequency: Inject three times daily subcutaneously, spaced at least 4 hours apart (morning, midday, bedtime). GHRP-6 has a short half-life of approximately 2.5 hours, making multiple daily injections more effective than once-daily dosing for sustained GH elevation. Each injection should be administered on an empty stomach (2 to 3 hours after meals, 30 minutes before eating) to maximize GH release.
On the master sheet
- Vial
- 5mg
- BAC
- 2mL
- Dose
- 100–300mcg 1–3x daily
- Route
- SubQ
- Cycle
- 6–12 wks
- Time Off
- 3–4 wks
- Bloodwork
- IGF-1, prolactin, cortisol
Side-effect family — GH Secretagogues (CJC, Ipa, GHRP): Water retention and bloat · Carpal tunnel or tingling hands · Increased hunger (GHRP-6) · Drowsiness. What helps, and the red flags →
Readers on GHRP-6
Questions and answers from readers, under generated names. Nothing here has been checked or reviewed by the site and none of it is medical advice. It is the least verified thing on this page — and it is here because people ask each other these things anyway, and most of the other places they can ask are run by sellers.
0 questions · 0 answers
No questions yet. Ask the first one above — it takes one box and an email address.
How names work, and the house rules
Names. Every verified address is given one generated name — two ordinary words — and keeps it. Nobody chooses a name and nobody can take another's. Posts marked desk were written by the site's own editorial desk, usually to open a thread; they carry a generated name like everyone else's and are held to the site's rules, which means they never state an amount.
What is not allowed. Selling, sourcing, vendor names, coupon codes and "message me" — posts that read that way are held and usually removed. Personal medical details you would not want public. Abuse. Instructions framed as what someone else should do.
What this is not. A reader's report of what happened to them is a report, not a finding, and an answer here is one person's view. Nothing in this section changes the evidence rating above it. If something you read here would change what you take, take it to a pharmacist or physician first.
Your data. Delete any post of yours at any time, or remove everything you have written together with your name. Details in the privacy notice.
Who should avoid it
- Active malignancy
- Pregnancy
- Hyperprolactinemia
- Diabetes
If used under medical supervision, monitor
- IGF-1, prolactin, cortisol
- Glucose
Regulatory & legal status
Not approved for human use in any major market.
Infographic
Where to read further
We link to live literature searches rather than a frozen citation list, so you always see current results — including anything published after our last review.
- PubMed — all published literature on GHRP-6
- PubMed — randomized controlled trials only
- ClinicalTrials.gov — registered human trials
Related peptides in Growth Hormone Axis
Terms used on this page
- Growth Hormone Secretagogue Receptor (GHS-R1a)
- GHS-R1a is the G protein-coupled ghrelin receptor mediating growth hormone release and appetite, notable for unusually high constitutive activity in the complete absence of any ligand.
- Off-Target Activity
- Off-target activity is any interaction a compound has with proteins other than its intended target, and it is a matter of degree rather than a property a drug either has or lacks.
- Prolactin
- Prolactin is a 199-amino-acid anterior pituitary hormone held under tonic dopamine inhibition, central to lactation and the marker of prolactinomas and drug-induced hyperprolactinaemia.
- Cortisol
- Cortisol is the principal human glucocorticoid, secreted by the adrenal cortex under ACTH control on a pronounced daily rhythm and carried in plasma largely bound to corticosteroid-binding globulin.
- Agonist
- An agonist is a ligand that binds a receptor and stabilises its active conformation, producing a biological response rather than merely occupying the binding site.
- Ghrelin
- Ghrelin is a 28-amino-acid stomach peptide that must carry an octanoyl group on serine 3 to activate GHS-R1a, where it drives both growth hormone release and appetite.
This page is educational information, not medical advice. It cannot account for your medical history, medications, or risk factors. Do not start, stop or change any treatment based on it. Speak to a qualified healthcare professional who knows your case.