Supplied ready in solution
Metabolic & Weight
At a glance
Ten answers, each one line. Open any row for the detail behind it.
What it does A single molecule that activates two incretin receptors.
A single molecule that activates two incretin receptors. In head-to-head and cross-trial comparison it produces the largest average weight loss of any approved pharmacotherapy, approaching the range of sleeve gastrectomy.
Half-life ~5 days — Documented
~5 days
Typical studied dose Set on the approved label, which states the starting dose, how it is… — On the label
Set on the approved label, which states the starting dose, how it is increased and the maximum. Read it there rather than anywhere else — including here.
How often it is used The label schedule is once weekly. Dosing intervals follow the half-life… — On the label
The label schedule is once weekly. Dosing intervals follow the half-life above, and the prescribing information is what sets them.
How it is taken Subcutaneous, once weekly — Documented
Subcutaneous, once weekly
Main side effects Thyroid C-cell tumor boxed warning · Pancreatitis and gallbladder events · Counterfeit market — Carries serious risk
Thyroid C-cell tumor boxed warning — Same rodent-derived contraindication as other incretin agonists: medullary thyroid carcinoma history or MEN2.
Pancreatitis and gallbladder events — Uncommon but serious; rapid weight loss increases gallstone formation.
Counterfeit market — Regulators have seized counterfeit tirzepatide vials; grey-market "research" tirzepatide has no identity or sterility assurance.
Storage before mixing Supplied already in solution and kept refrigerated, not frozen. Freezing…
Supplied already in solution and kept refrigerated, not frozen. Freezing a protein solution can aggregate it, which is not always visible.
Shelf life after mixing Nothing to mix — it is not supplied as a powder. The relevant date is…
Nothing to mix — it is not supplied as a powder. The relevant date is the one printed on the product.
Evidence level 5/5 · Very strong — Documented
Multiple phase 3 randomized trials plus regulatory approval in a major market.
Regulatory status FDA Approved — Documented
FDA-approved for type 2 diabetes, chronic weight management, and obstructive sleep apnea in obesity Prescription drug. FDA has stated tirzepatide is no longer in shortage, which sharply restricts lawful compounding.
Overview
A single molecule that activates two incretin receptors. In head-to-head and cross-trial comparison it produces the largest average weight loss of any approved pharmacotherapy, approaching the range of sleeve gastrectomy.
FDA ApprovedFDA-approved for type 2 diabetes, chronic weight management, and obstructive sleep apnea in obesity
| Regulatory status | FDA-approved for type 2 diabetes, chronic weight management, and obstructive sleep apnea in obesity |
|---|---|
| Drug class | Dual GIP / GLP-1 receptor agonist — 39-amino-acid acylated peptide |
| Route | Subcutaneous, once weekly |
| Half-life | ~5 days |
| Evidence rating |
5/5 Very strong
Evidence rating 5 out of 5: Very strong
Multiple phase 3 randomized trials plus regulatory approval in a major market. |
| Studied in | SURPASS program (type 2 diabetes), SURMOUNT program (obesity, sleep apnea, heart failure), SURPASS-CVOT (cardiovascular outcomes). |
Tirzepatide sequence & structure
Tirzepatide is a 39-residue linear peptide with a C-terminal amide, carrying a fatty-acid side chain, non-standard residues; molecular weight 4,813.53 Da.
* K: 2×OEG-γGlu-C20 diacid
[bracketed] = non-standard residue* = side-chain modification
| Three-letter | H-Tyr-Aib-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Tyr-Ser-Ile-Aib-Leu-Asp-Lys-Ile-Ala-Gln-Lys(2×OEG-γGlu-C20 diacid)-Ala-Phe-Val-Gln-Trp-Leu-Ile-Ala-Gly-Gly-Pro-Ser-Ser-Gly-Ala-Pro-Pro-Pro-Ser-NH2 |
|---|---|
| Length | 39 amino acid residues |
| Modifications |
|
| Molecular formula | C225H348N48O68 |
| Molecular weight | 4,813.53 Da (average, free base) |
| Identifiers | CAS 2023788-19-2 · DrugBank DB15171 |
| Sources | DailyMed — MOUNJARO (tirzepatide) injection prescribing information, section 11 DescriptionFDA — MOUNJARO original approval label (2022, NDA 215866), section 11 DescriptionKEGG DRUG D11360 Tirzepatide (JAN/USAN): sequence, formula, MW 4813.45ChEMBL CHEMBL4297839 (biotherapeutic sequence, Lys20 modified)EMA — Mounjaro EPAR public assessment report, 2.4.2 Active Substance |
Single-chain synthetic (SPPS) 39-mer derived from human GIP(1-39) with Aib2/Aib13 and Asp20→Lys for the lipid side chain; supplied as the free peptide in a phosphate-buffered solution (Mounjaro/Zepbound), so 'tirzepatide sodium' listings refer to the same molecule. MW is quoted as 4813.53 Da in the FDA label and 4813.45 Da (average) by KEGG and the EMA EPAR; all give C225H348N48O68. UNII OYN3CCI6QE (FDA GSRS, base sequence YAEGTFTSDYSIGLDKIAQKAFVQWLIAGGPSSGAPPPS with the three modifications applied). PubChem holds two distinct depositor structures for this name (CID 156588324 with InChIKey AAPYRSPHYSKGIS-..., titled 'Tirzepatide', and CID 166567236, linked from KEGG and Wikipedia, InChIKey BTSOGEDATSQOAF-...) that differ in where the acyl chain is drawn; neither could be confirmed against the Lys20 structure, so no CID is given.
Record confidence: high — two independent authoritative sources agree on the sequence and modifications. Every sequence on the site is listed with its sources on the peptide sequences index.
How it works
Agonises both the GIP and GLP-1 receptors. GLP-1 activity drives satiety and glucose-dependent insulin release; the added GIP component appears to improve insulin sensitivity, adipose handling of nutrients, and may blunt GLP-1-related nausea, allowing higher effective dosing.
Evidence base
Rated 5 of 5 — Very strong. Multiple phase 3 randomized trials plus regulatory approval in a major market.
- Multiple phase 3 trials with active comparators, not just placebo.
- Sleep apnea approval was based on a dedicated randomized trial with objective polysomnography endpoints.
Benefits and risks, weighed against the evidence
Every entry below carries the strength of the evidence behind it — three bars for strong human data, two for moderate, one for preliminary or preclinical work. The two columns are not equal by design: where a compound has more documented risk than demonstrated benefit, the lists say so.
Reported benefits
5 entries · 3 on strong human evidence
-
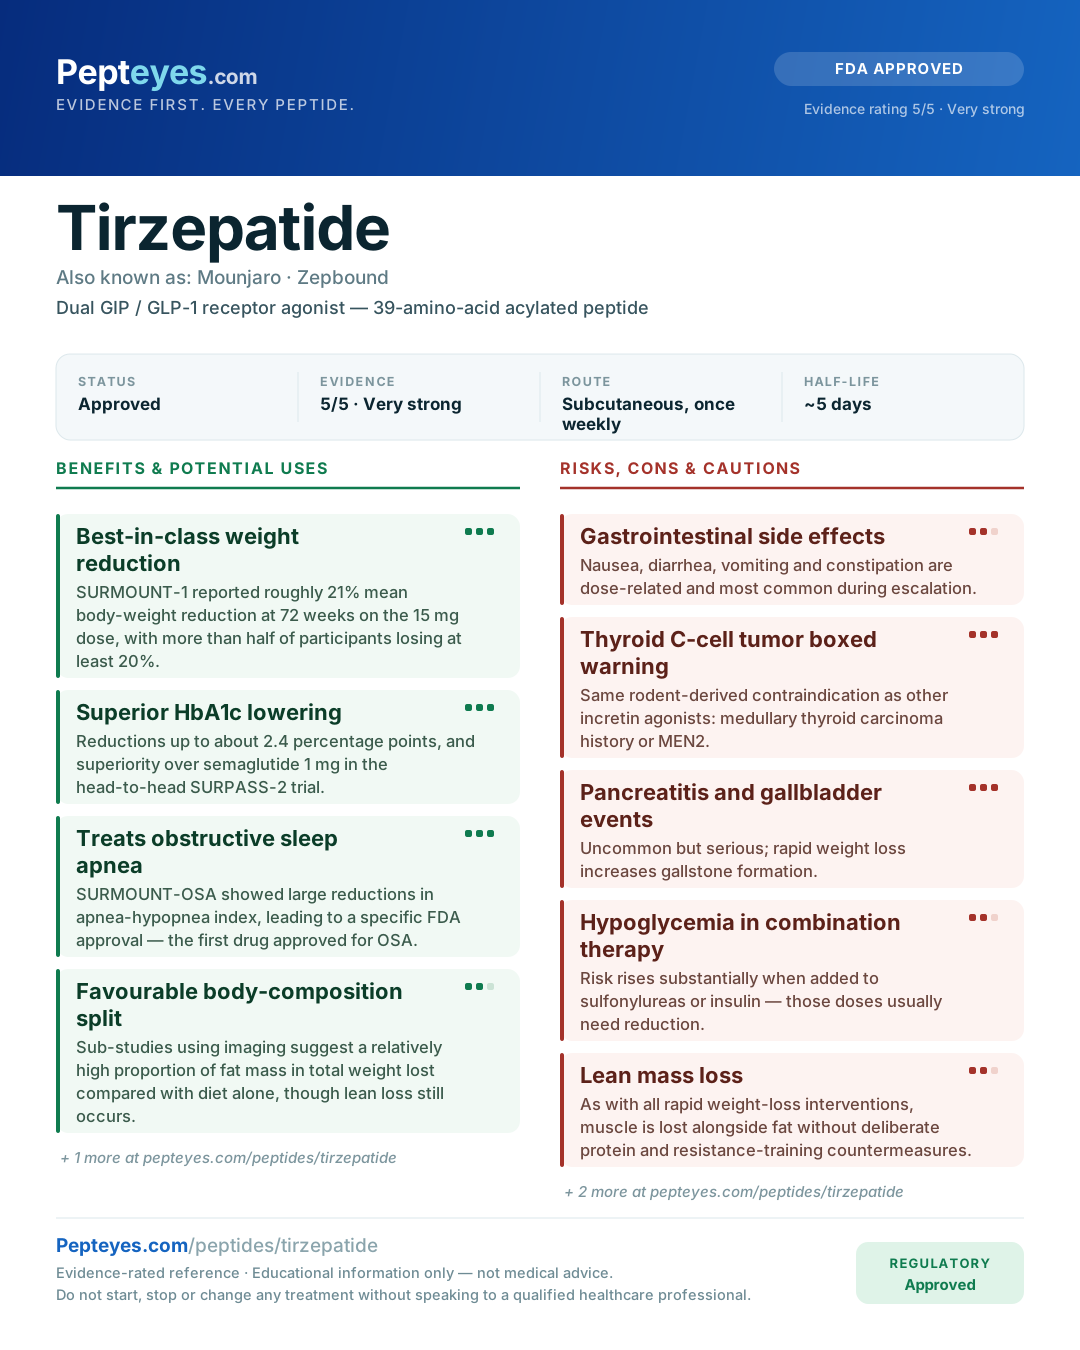
Best-in-class weight reduction
SURMOUNT-1 reported roughly 21% mean body-weight reduction at 72 weeks on the 15 mg dose, with more than half of participants losing at least 20%.
Evidence: Strong evidence -
Superior HbA1c lowering
Reductions up to about 2.4 percentage points, and superiority over semaglutide 1 mg in the head-to-head SURPASS-2 trial.
Evidence: Strong evidence -
Treats obstructive sleep apnea
SURMOUNT-OSA showed large reductions in apnea-hypopnea index, leading to a specific FDA approval — the first drug approved for OSA.
Evidence: Strong evidence -
Favourable body-composition split
Sub-studies using imaging suggest a relatively high proportion of fat mass in total weight lost compared with diet alone, though lean loss still occurs.
Evidence: Moderate evidence -
Blood pressure and lipid improvement
Consistent reductions in systolic blood pressure and triglycerides across the phase 3 program.
Evidence: Moderate evidence
Risks and cautions
7 entries · 3 serious or common
-
Gastrointestinal side effects
Nausea, diarrhea, vomiting and constipation are dose-related and most common during escalation.
Evidence: Moderate evidence -
Thyroid C-cell tumor boxed warning
Same rodent-derived contraindication as other incretin agonists: medullary thyroid carcinoma history or MEN2.
Evidence: Serious -
Pancreatitis and gallbladder events
Uncommon but serious; rapid weight loss increases gallstone formation.
Evidence: Serious -
Hypoglycemia in combination therapy
Risk rises substantially when added to sulfonylureas or insulin — those doses usually need reduction.
Evidence: Moderate evidence -
Lean mass loss
As with all rapid weight-loss interventions, muscle is lost alongside fat without deliberate protein and resistance-training countermeasures.
Evidence: Moderate evidence -
Anesthesia and aspiration risk
Delayed gastric emptying warrants pre-procedure planning.
Evidence: Moderate evidence -
Counterfeit market
Regulators have seized counterfeit tirzepatide vials; grey-market "research" tirzepatide has no identity or sterility assurance.
Evidence: Serious
Counts are not a score. A single serious risk can outweigh several well-supported benefits, and a long benefit list built on preclinical work outweighs nothing at all.
Opinion — what people actually report
7 themes · 2 reported benefits · 3 reported problems
This is the weakest tier on this site. These are themes drawn from public discussion — forums, subreddits and patient threads — not from trials. There is no control group, no denominator, and no way to confirm that what someone injected matched its label. People post when a result is dramatic and when something goes wrong, and rarely when nothing happens, so treat everything below as a description of the conversation rather than of the compound. The bars count how often a thing is said, not how well it is supported.
-
Consistently described as stronger than semaglutide Reported benefit. Dominant theme: Comes up in most discussions of this compound.
The dominant comparison in every forum where both are discussed. People switching typically report both more weight loss and, unexpectedly to them, less nausea — which is the opposite of what they assumed a stronger drug would do.
-
Easier on the stomach than expected Reported benefit. Recurring: Raised regularly, though not by everyone.
The GIP component is widely credited by the better-informed posters. Whatever the mechanism, the reported tolerability advantage over semaglutide is one of the most consistent themes in the space.
-
Sulphur burps and constipation Reported problem. Recurring: Raised regularly, though not by everyone.
The two complaints that survive the comparison. Constipation in particular is described as the effect people manage indefinitely rather than adapt out of.
-
Fatigue in the first weeks Reported problem. Recurring: Raised regularly, though not by everyone.
Frequently attributed by posters to eating far less rather than to the drug, and usually reported to resolve once intake stabilises.
-
Vial-versus-pen and compounded supply dominate Practical note. Dominant theme: Comes up in most discussions of this compound.
A large share of all discussion is logistics: pharmacy stock, cost, compounded sources and how to tell a real vial from a counterfeit. The consistent warning is that this is where the actual risk sits, not in the molecule.
-
Micro-dosing and stretching the schedule Practical note. Recurring: Raised regularly, though not by everyone.
Very commonly discussed as a cost strategy and as a way to hold a maintenance weight. It is off-label improvisation, and the more careful posters say so.
-
Injection site lumps and bruising Reported problem. Occasional: Reported by a minority, or in specific contexts.
Minor and usually attributed to technique or to injecting cold solution.
Where the reports and the evidence part ways
The community's core claim — that tirzepatide outperforms semaglutide — is one of the few forum consensuses that a head-to-head randomized trial actually confirmed: SURMOUNT-5 found substantially greater weight loss on tirzepatide. Where the accounts drift is dose. Forums treat the top dose as the goal, while the trials show much of the benefit arrives at intermediate doses and the marginal gain from escalating further is smaller than the discussion implies. The tolerability advantage people report is also less clear-cut in trial data than in forums, where it is close to an article of faith. And the widespread confidence that the GIP component explains the reduced nausea is a plausible hypothesis being repeated as an established fact; it is not settled.
Cheat sheet
The full sheet, all 77 compounds →The community reference numbers for this compound — reconstitution, working dose, cycle and bloodwork. Research and education only, not medical advice, and not part of the evidence-rated monograph above. Doses assume a 1mL / 100-unit insulin syringe — the calculator does the units for you.
Protocol overview
Dosing & reconstitution 10 mg vial
| PHASE | WEEKLY DOSE | UNITS PER INJECTION |
|---|---|---|
| Weeks 1 to 4 | 2.5 mg | 25 units (0.25 mL) x 1 |
| Weeks 5 to 8 | 5 mg | 50 units (0.50 mL) x 1 |
| Weeks 9 to 12 | 7.5 mg | 37.5 units (0.38 mL) x 2 |
| Weeks 13 to 16 | 10 mg | 50 units (0.50 mL) x 2 |
Frequency: Inject once weekly subcutaneously on the same day each week. For doses requiring multiple injections, administer consecutively at different sites. Dose increases occur every 4 weeks to minimize gastrointestinal side effects. Higher doses (12.5 to 15 mg/week) may be used in subsequent phases if tolerated and clinically indicated.
On the master sheet
- Vial
- 10mg
- BAC
- 2mL
- Dose
- 2.5–15mg weekly (titrate)
- Route
- SubQ
- Cycle
- 12–16+ wks
- Time Off
- None fixed
- Bloodwork
- Same as sema
Storage note: Very stable. 4–6 weeks reconstituted. Full storage guide →
Side-effect family — GLP-1s (Sema, Tirz, Reta): Nausea and vomiting · Constipation or diarrhea · Muscle loss · Injection site redness or a lump. What helps, and the red flags →
Readers on Tirzepatide
Questions and answers from readers, under generated names. Nothing here has been checked or reviewed by the site and none of it is medical advice. It is the least verified thing on this page — and it is here because people ask each other these things anyway, and most of the other places they can ask are run by sellers.
1 question · 1 answer
-
Pearl Cloud desk — written by the site's editorial desk asked
Anyone switched from semaglutide to tirzepatide — was it really easier on the stomach, or is that a forum myth?
Reply
Show 1 answerCollapse 1 answer
- Yellow Vale desk — written by the site's editorial desk answered
The switch report is one of the most consistent things in the GLP-1 threads: more loss, and — to people's surprise — less nausea. The trial picture is only half of that. The one head-to-head in obesity found more weight loss on tirzepatide, but stomach side effects were about the same on both.
So the extra weight loss is real, and the "gentler" part is mostly people comparing a second drug, started with a stomach that had already adapted, against their memory of the first.
How names work, and the house rules
Names. Every verified address is given one generated name — two ordinary words — and keeps it. Nobody chooses a name and nobody can take another's. Posts marked desk were written by the site's own editorial desk, usually to open a thread; they carry a generated name like everyone else's and are held to the site's rules, which means they never state an amount.
What is not allowed. Selling, sourcing, vendor names, coupon codes and "message me" — posts that read that way are held and usually removed. Personal medical details you would not want public. Abuse. Instructions framed as what someone else should do.
What this is not. A reader's report of what happened to them is a report, not a finding, and an answer here is one person's view. Nothing in this section changes the evidence rating above it. If something you read here would change what you take, take it to a pharmacist or physician first.
Your data. Delete any post of yours at any time, or remove everything you have written together with your name. Details in the privacy notice.
Who should avoid it
- Medullary thyroid carcinoma or MEN2 history
- Pregnancy
- Severe gastroparesis
- Prior pancreatitis (relative)
If used under medical supervision, monitor
- HbA1c, glucose
- Weight and lean mass
- Hydration and renal function
- Concomitant insulin/sulfonylurea dosing
Interactions
Not exhaustive. Always have a pharmacist or physician review your full medication list — including supplements.
- Insulin and sulfonylureas — hypoglycemia risk rises substantially; doses typically need reducing
- Oral contraceptives — reduced effectiveness around dose escalation; a barrier method is advised for 4 weeks after each increase
- Oral medications generally — delayed gastric emptying affects absorption
- Anesthesia — pre-procedural withholding guidance applies
- Thiamine - of the fifteen cases of Wernicke encephalopathy reported on GLP-1 drugs in a pharmacovigilance analysis, six were on tirzepatide, second only to semaglutide, and nearly all patients had weight loss, vomiting, appetite loss or malnutrition beforehand. Lasting neurological damage was recorded in most of those followed up. Rare, but the prodrome is ordinary.
- Oral supplements and the timing of the delay - the slowing of gastric emptying is largest after the first dose and shrinks with repeated dosing, which is why an early dose halved the peak concentration of paracetamol while the effect had gone by the fourth week. Anything swallowed for an effect that depends on peak concentration is most affected at the start and after each increase.
- Protein intake - lean soft tissue made up roughly a quarter to two fifths of the weight lost across recent trials of this class, and a survey of people using these drugs found most below the protein intakes associated with preserving it. The randomised test of whether supplementing protein, with or without resistance training, changes that is under way and has not reported.
- Micronutrient status - in a large claims analysis of adults starting GLP-1 drugs, a nutritional deficiency was recorded in over a fifth within a year, vitamin D most commonly, against a background of substantially reduced energy intake. Claims record diagnoses rather than measured status, and detection effort is part of the signal.
- Creatine - raises serum creatinine without a matching fall in directly measured filtration, so a creatinine-based estimate of kidney function reads low in someone taking it. That matters on a drug whose gastrointestinal effects can cause the dehydration that renal monitoring is there to catch.
- Berberine - sold as a natural version of these drugs. Its pooled weight effect is around a kilogram, and it does not act on appetite the same way. The documented hazard is different: repeated berberine reduced CYP2D6, CYP2C9 and CYP3A4 activity in a controlled human study, so it interacts with other medicines rather than with this one.
Commonly confused with
These mix-ups cause real harm — two products sold under one name, or two molecules whose effects run in opposite directions.
Retatrutide adds a third receptor (glucagon) and shows larger phase 2 weight loss, but it is unapproved and has no phase 3 safety data. Tirzepatide is an approved drug; retatrutide is not.
Compare side by sideRegulatory & legal status
Prescription drug. FDA has stated tirzepatide is no longer in shortage, which sharply restricts lawful compounding.
Infographic
What this entry was checked against
The specific records this monograph was verified against on its last research pass. We link live literature searches below as well, because these are a snapshot and the literature is not.
- MOUNJARO (tirzepatide) FDA prescribing information - section 7.2 and the interaction studies: oral contraceptive peak concentrations cut by more than half and exposure by about a fifth after a single dose, paracetamol peak halved after the first dose with no meaningful effect by week four, and the statement that the gastric emptying delay is largest after the first dose
- Lev D et al. Glucagon-like peptide-1 receptor agonists and Wernicke encephalopathy: a pharmacovigilance study and literature review. Clin Nutr 2026;57:106571 - six of fifteen cases on tirzepatide
- Nutritional deficiencies and muscle loss in adults with type 2 diabetes using GLP-1 receptor agonists: a retrospective observational claims study of 461,382 adults
- Preservation of lean soft tissue during weight loss induced by GLP-1 and GLP-1/GIP receptor agonists: a case series - lean soft tissue loss comprised 26-40% of weight loss in recent trials
- LEAN-PREP: lean mass preservation with resistance exercise and protein during semaglutide and tirzepatide therapy - published protocol; no results yet
- Naeini EK et al. Effect of creatine supplementation on kidney function: a systematic review and meta-analysis. BMC Nephrol 2025;26:622
- Guo Y et al. Repeated administration of berberine inhibits cytochromes P450 in humans. Eur J Clin Pharmacol 2012;68:213-7
Where to read further
We link to live literature searches rather than a frozen citation list, so you always see current results — including anything published after our last review.
- PubMed — all published literature on Tirzepatide
- PubMed — randomized controlled trials only
- ClinicalTrials.gov — registered human trials
- DailyMed — official FDA prescribing information
Related peptides in Metabolic & Weight
Terms used on this page
- The Incretin Effect
- The incretin effect is the larger insulin response to oral glucose than to intravenous glucose matched for the same blood glucose profile, and it is mediated mainly by GLP-1 and GIP.
- Insulin Resistance
- Insulin resistance is a state in which a given insulin concentration produces less than the expected effect on glucose uptake, hepatic glucose output or lipolysis.
- Glucose-Dependent Insulin Secretion
- Glucose-dependent insulin secretion is beta-cell insulin release that scales with ambient glucose, so incretin amplification fades as concentrations approach the normal range.
- Satiety vs Satiation
- Satiation is the set of signals that ends a meal in progress, while satiety is the post-meal inhibition that determines how long it takes before eating begins again.
- Glucagon-Like Peptide-1 (GLP-1)
- Glucagon-like peptide-1 is an incretin hormone released by intestinal L-cells after a meal that stimulates glucose-dependent insulin secretion and suppresses appetite.
- Phase 3 Trial
- A Phase 3 trial is the large confirmatory study, powered for a prespecified clinical endpoint, on which a marketing application and the resulting product label are built.
This page is educational information, not medical advice. It cannot account for your medical history, medications, or risk factors. Do not start, stop or change any treatment based on it. Speak to a qualified healthcare professional who knows your case.